Making Every Step of Chronic Care Safer: Patients as Partners in Medication, Referral, and Follow-up
Original Chinese title: 把安全做進每一次慢性病照護:從用藥、轉診到長期追蹤,病人如何成為照護團隊的一員?
World Patient Safety Day 2026 focuses on safe care for noncommunicable diseases. Medication, referral, handoff, and follow-up require patient partnership backed by accountable health systems.
鄭淑禎|實踐大學專任助理教授
An assistant professor at Shih Chien University focused on long-term care, public service design, industrial change, and how systems work for users and frontline teams.
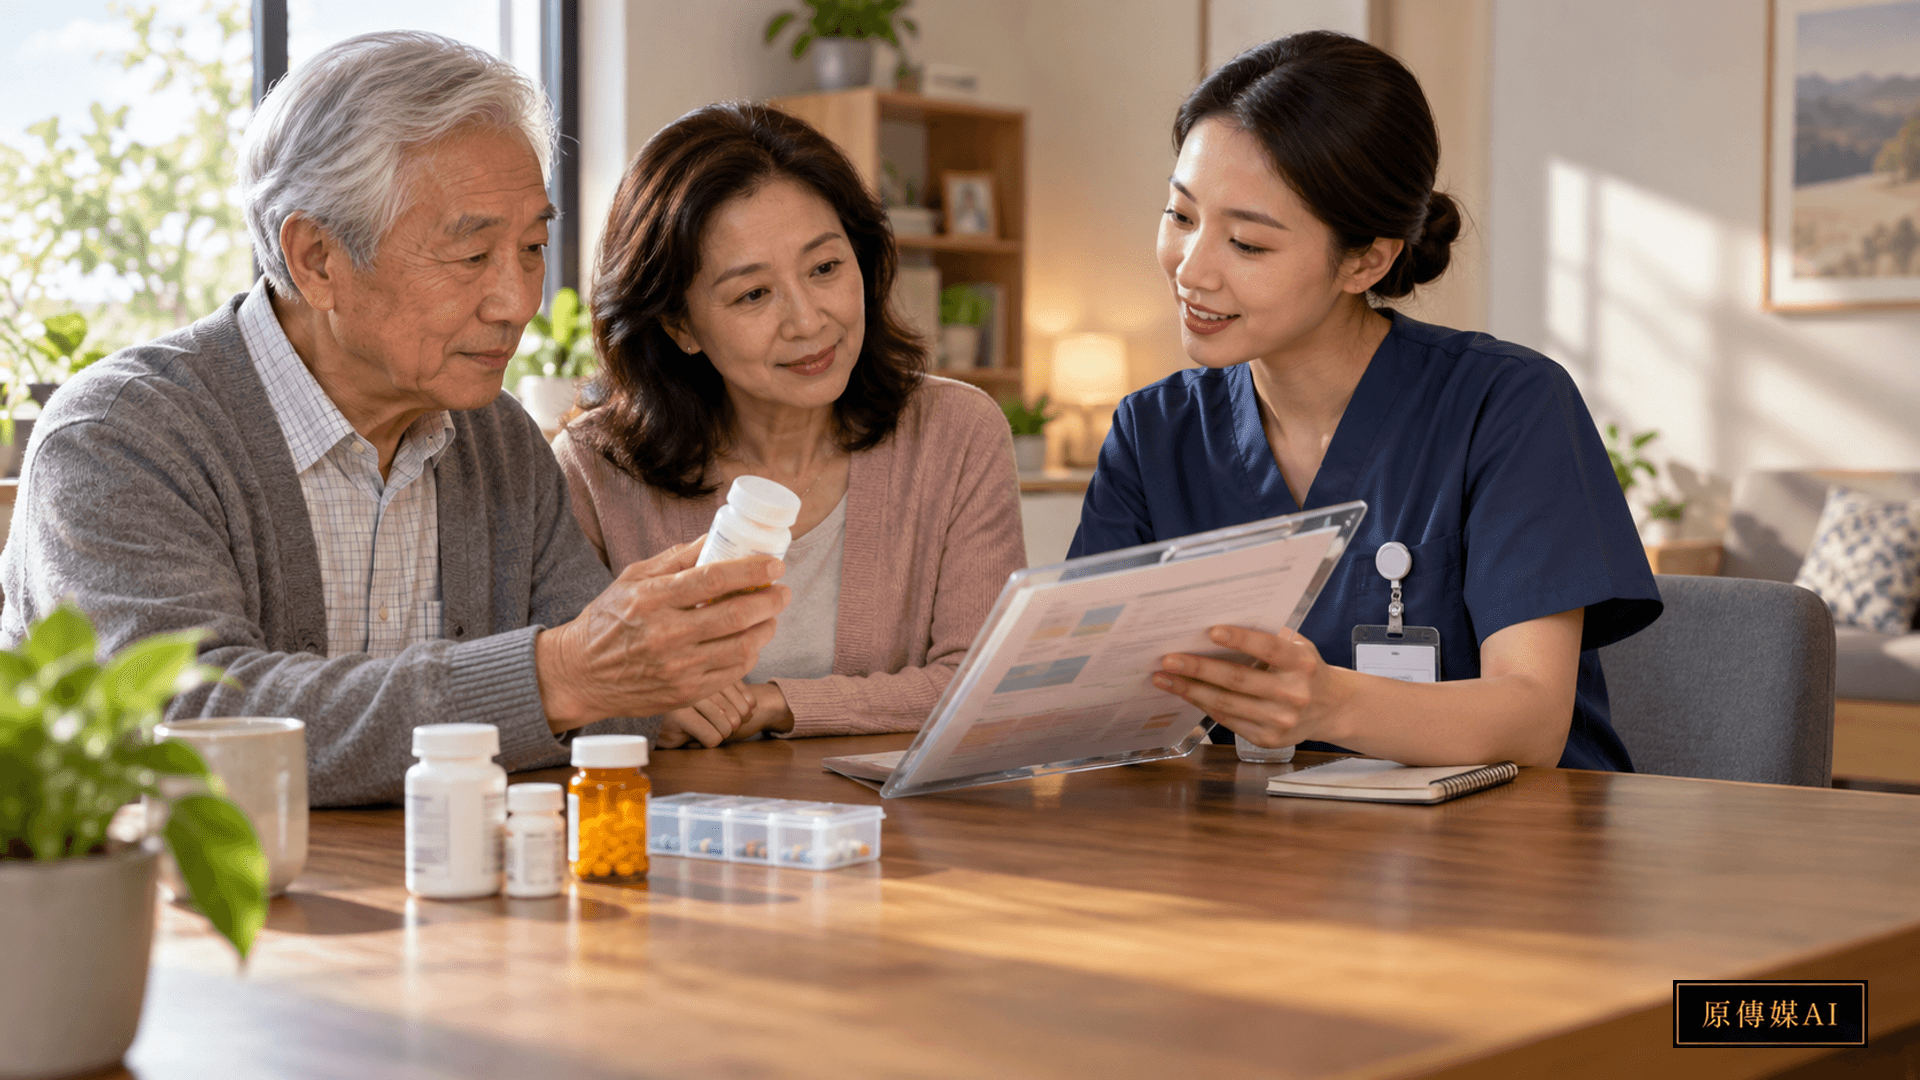
# Making Every Step of Chronic Care Safer: Patients as Partners in Medication, Referral, and Follow-up
Risk hides in transitions
A person may change medication at a clinic, have tests at a hospital, and collect medicines at a community pharmacy. Who reconciles old and new prescriptions, explains results, and confirms a referral was completed? Small information gaps can accumulate over years. World Patient Safety Day 2026 focuses on noncommunicable diseases because they often require long, cross-setting care.
A campaign requires institutional action
WHO’s “Safe care for life” campaign covers prevention, diagnosis, treatment, long-term management, and self-care. It calls on clinicians, managers, policy makers, and patients to communicate, manage transitions, and sustain follow-up. These are principles and calls to action, not evidence that every facility has achieved them. Patient engagement does not transfer system responsibility to the patient.
A medication list needs an owner
WHO’s technical report on medication safety in transitions of care describes discrepancies around admission, discharge, and transfer. Formal processes, trained staff, patient and family partnership, and measurement are needed. Names, doses, timing, discontinuation reasons, allergies, and non-prescription products may matter. Patients can carry a list, but clinicians and pharmacists must reconcile conflicts rather than asking patients to guess or stop a medicine themselves.
Self-care must be supported
WHO includes long-term management and self-care, but patients need accurate information, supplies, and reachable professional support. They can record symptoms, ask about warning signs, and confirm visits; they cannot assess every drug interaction or interpret every test alone. Labeling a missed appointment as noncompliance may hide transport cost, lost wages, care duties, language barriers, or booking failures. These are service-design signals.
Referral is more than a form
A safe referral has a clear purpose and urgency, an informed receiving team, and a patient who knows when and whom to contact. Pending results need an owner and deadline. Caregivers may help with questions, transport, and scheduling with the patient’s consent. Language, mobility, digital access, and cost require alternatives to an online-only notice.
Confirm the handoff
Nursing shifts, hospital discharge, and specialist-to-primary-care transfers can lose information. A handoff should cover current condition, medication changes, pending tests, warning signs, and the next responsible person. Sending a file is not the same as confirming that it was understood. Useful measures include completed referrals, unresolved results, medication discrepancies, and patient-reported confusion.
Patient experience is safety information
Patients may first notice conflicting advice, a changed medicine, or an unavailable follow-up appointment. WHO asks systems to include lived experience in service design and care. A report needs an accessible channel, traceable response, and a culture that does not blame the person who speaks up. Caregiver observations should be distinguished from the patient’s wishes and clinical judgment.
Two-Eyed Seeing: two-way knowledge between clinic and daily life
Clinicians see tests, readings, and prescriptions; patients know commuting time, work shifts, care duties, side effects, and what they can understand. When a plan is infeasible, teams should ask why and discuss alternatives. In rural and Indigenous communities, local workers and patients should examine language, distance, and cultural safety rather than copying an international campaign as a ready-made local workflow.
Map an encounter as a timeline
Safety failures often happen after a person leaves one service but before another has truly received them. A shared timeline can show prescription changes, tests, result dates, referral confirmation, and whom to call if no notice arrives. It should distinguish patient actions from institutional duties. Long-term care, home nursing, and pharmacies belong on the map because medicines and symptoms are managed outside hospitals.
Caregiver participation requires consent
Caregivers may notice nighttime dizziness or medication difficulty and help with travel. Families differ, and not every patient has someone available. Teams should ask what information the patient wishes to share and with whom, then provide understandable explanations. People living alone or with overburdened caregivers need service alternatives. Respect for autonomy and access must be part of safety.
Turn complaints into learning measures
Patient reports can reveal incomplete referrals, unreturned abnormal tests, conflicting medication lists, or unclear warning signs. Measures should be examined by language, disability, age, and location; better averages can hide those excluded. Reporting should repair processes rather than blame an individual. Resending the same complicated document does not resolve “I do not know what happens next.”
Resources for local implementation in Taiwan
International principles are a checklist, not an identical workflow for every part of Taiwan. Travel, language, long-term care links, and hospital data rules vary. A pilot can map one common referral route with clinics, hospitals, pharmacies, community workers, and patients, then document gaps before expanding. Budgeting must include people who answer questions and track results, not merely software.
Keep accountability within the system
A practical safety promise names who checks medicines, follows tests, confirms referrals, responds to deterioration, and handles corrections. WHO’s global action plan places responsibility across policy and clinical systems. Patient questions can reveal gaps earlier, but they cannot replace staffing, training, information exchange, or accountable processes.
Continue asking from your role
- People living with chronic conditions: Ask about evidence, limits, and practical action.
- Family caregivers: Ask about evidence, limits, and practical action.
- Clinical and pharmacy staff: Ask about evidence, limits, and practical action.
- Health policy and service designers: Ask about evidence, limits, and practical action.
Sources and further reading
Role-Driven Inquiry
Yuan Media AI | Guided Questions by Role
Select a role first, then review the complete questions from that perspective; clicking a question will display Yuan Media AI’s response in real time.
Select a role
People living with chronic conditions
Examine the article's evidence, governance boundaries, data rights, and actionable steps from the perspective of a People living with chronic conditions.
Choose a question
AI use and content-safety disclosure
This article draws on official and research sources. Evidence, limitations, and analysis are distinguished. The cover is an AI-assisted concept image.